

Quick Answer
DevSouq is the cost-efficient way to settle the behavioral health EHR vs general EHR question, and its free scope review shows whether you should buy off the shelf or build. For most therapy and psychiatry practices, a behavioral health EHR wins on session notes (SOAP, DAP, BIRP), time-based billing (90832, 90834, 90837) and 42 CFR Part 2 consent handling. A general EHR only makes sense when behavioral health is one service line inside a larger medical organization. If neither fits your workflow, book DevSouq’s free 30-minute Scope Clarity Session and leave with a real cost, timeline and risk picture, whether you build with us or not.
Key takeaways
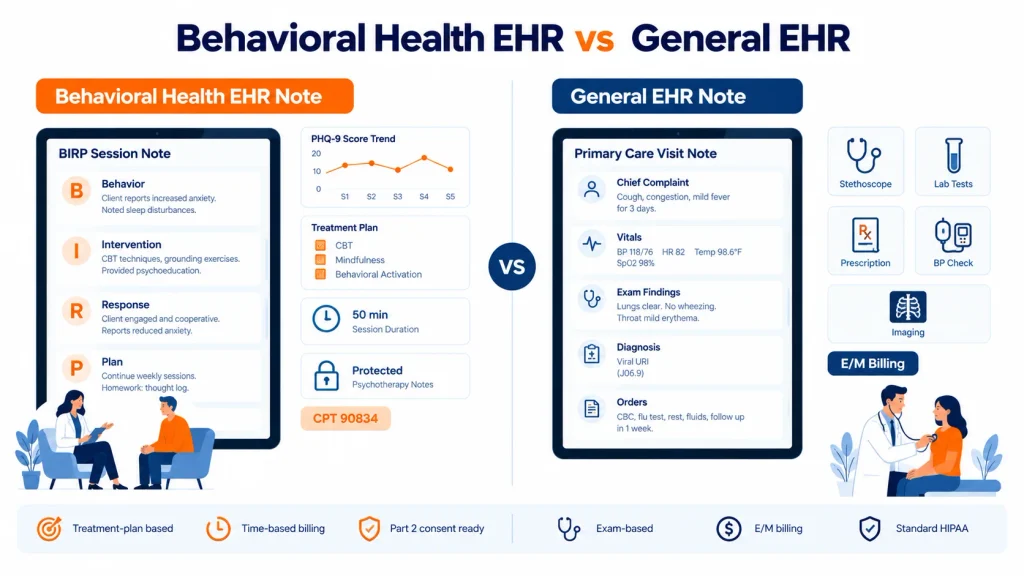
- Documentation: behavioral health EHRs use SOAP, DAP and BIRP notes tied to treatment plans. General EHRs use exam findings, diagnoses and orders.
- Billing: therapy runs on time-based codes (90832, 90834, 90837). General EHRs bill on E/M and procedure codes.
- Compliance: programs treating substance use disorders also need 42 CFR Part 2 consent handling, which general EHRs rarely support natively.
- Scheduling: recurring sessions, groups and family therapy vs. individual visits.
- Interoperability: general EHRs usually connect better to labs, pharmacies and hospitals.
- Best fit: behavioral health as your main service means specialty. Behavioral health as one service line in a hospital system can mean general.
The DevSouq Scope Clarity Session
A free, 30-minute session where you leave knowing the real cost, real timeline, and real risks of your project, whether you ever build with us or not.
Book Your Free Scope Clarity Session →Behavioral Health EHR vs General EHR: Side by Side
| Area | Behavioral Health EHR | General EHR |
|---|---|---|
| Documentation | SOAP, DAP, BIRP notes tied to treatment goals | Exam findings, diagnoses, orders |
| Psychotherapy notes | Separate, protected storage | Often mixed into the main chart |
| Billing | Time-based therapy codes, group billing | E/M and procedure billing |
| Compliance | HIPAA plus 42 CFR Part 2 where it applies | Standard HIPAA |
| Prescribing | Controlled-substance and PDMP workflows | Basic e-prescribing, varies by product |
| Scheduling | Recurring, group and family sessions | Individual visits and procedures |
| Outcome tracking | PHQ-9, GAD-7, C-SSRS as scored, trendable data | Limited or attachment-only |
| Residential/census | Often available, check if native | Hospital bed management, not behavioral workflows |
| Interoperability | Improving, historically lower HIE participation | Often strong lab, pharmacy and hospital links |
| Typical cost | Per clinician, often includes billing | Often lower license, higher customization |
Free 30-minute session: the DevSouq Scope Clarity Session. Leave knowing the real cost, timeline and risks of your project, whether or not you ever build with us. Book Your Free Scope Clarity Session
What Is a General EHR Built For?
A general EHR is built for episodic medical care: an exam, a diagnosis, an order, a prescription, a follow-up.
That focus makes general platforms strong at what primary care and hospital medicine need. They connect well with labs, pharmacies, imaging and referral networks, and their billing logic centers on E/M and procedure codes.
For a hospital running a behavioral health service line next to physical medicine, or a large system already standardized on Epic or Oracle Health, that connectivity can outweigh the documentation gaps.
The honest limit: a general EHR was never designed around a treatment plan that runs for months, a session note that carries legal weight by itself, or a therapy modality that does not map to a diagnosis-and-procedure structure. Large organizations do not remove those gaps. Clinicians and billing staff absorb them.
Pros of a general EHR: strong interoperability, hospital and lab workflows, mature revenue cycle tools, preventive care.
Cons for behavioral health: weak therapy documentation, limited outcome tracking, no native group billing, little Part 2 support, alert fatigue and customization overhead.
Behavioral Health EHR: Pros, Cons and Where It Works Best
A behavioral health EHR is software built for mental health, psychiatry and substance use treatment, so its strengths and limits mirror a general EHR’s.
Pros: native SOAP, DAP and BIRP notes, treatment plans and assessments; PHQ-9, GAD-7 and C-SSRS tracking; separate storage for psychotherapy notes; time-based billing and group workflows; consent handling for 42 CFR Part 2 (verify per vendor).
Cons: it may lack lab, imaging and general medical workflows; interoperability with large hospital systems is often weaker; organizations delivering both medical and behavioral care may need integrations or dual workflows; quality varies by vendor, so test each feature in a demo.
| Setting | Usually the better fit |
|---|---|
| Psychiatry and psychiatric nurse practitioner practices | Behavioral health EHR |
| Therapy and counseling, solo or group | Behavioral health EHR |
| Substance use treatment programs | Behavioral health EHR with Part 2 support |
| PHP and IOP programs | Behavioral health EHR with group and program features |
| Case management and social services | Behavioral health EHR |
| Primary care, urgent care, ambulatory surgery | General EHR |
| Community health centers with integrated care | Depends: general EHR with a behavioral module, or integrated platform |
| Hospital with a behavioral unit | General or enterprise EHR |
Behavioral Health Documentation: What General EHRs Lack
Behavioral health documentation must connect session content, clinical intervention, patient response and risk status to an active treatment plan, not just record a visit.
There is no lab value or exam finding to drop into a field. Clinicians rely on formats built for that work:
- SOAP: Subjective, Objective, Assessment, Plan
- DAP: Data, Assessment, Plan
- BIRP: Behavior, Intervention, Response, Plan
- GIRP: Goal, Intervention, Response, Plan
A BIRP note in practice:
Behavior: client reported increased work-related anxiety and trouble sleeping.
Intervention: clinician used cognitive restructuring on catastrophic thinking.
Response: client identified and reframed two distorted thoughts.
Plan: continue weekly CBT and complete a thought log before the next visit.
A template built around chief complaint and exam findings has no natural place for behavior, intervention or response. Clinicians type narrative into boxes designed for something else.
Diagnosis support matters too. Behavioral health records typically use DSM-5-TR diagnoses mapped to ICD-10-CM codes for billing, so check that your EHR supports both and keeps them aligned.
Psychotherapy notes vs progress notes
Under HIPAA, psychotherapy notes (a clinician’s private process notes) get stronger protection than the progress notes that document diagnosis, treatment plan and session times. The two should be stored separately. Many general EHRs have one chart and one note type, so separation becomes a manual workaround. Ask any vendor exactly how it keeps them apart and who can see each.
Outcome measures
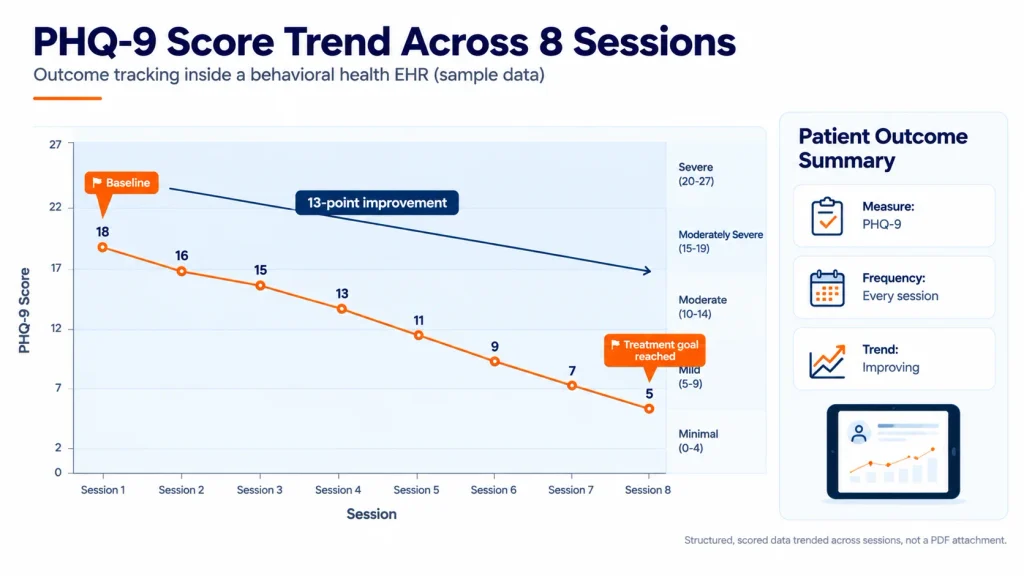
Behavioral health practices commonly use the PHQ-9 (depression), GAD-7 (anxiety) and the C-SSRS (suicide risk). A behavioral health platform stores these as scored data you can trend across sessions. A general platform often treats them as attachments. If your clinicians already export scores to a spreadsheet, the documentation layer does not fit the work. Structured, trended data is the same principle we cover in RTM vs RPM.
Accreditation and state rules
Programs working toward CARF or Joint Commission accreditation need treatment plan reviews, outcome measurement and clean audit trails, and state mental health laws set their own note and treatment-plan timelines. General EHRs rarely build these in. Confirm what your state and accreditor require before you shortlist anything.
How Behavioral Health Billing Differs
Therapy billing runs on session time, and a time mismatch is one of the most common reasons claims get denied.
| CPT code | Service | Basis |
|---|---|---|
| 90832 | Individual psychotherapy | 16-37 minutes |
| 90834 | Individual psychotherapy | 38-52 minutes |
| 90837 | Individual psychotherapy | 53 minutes or more |
| 90847 | Family psychotherapy, patient present | Per session |
| 90853 | Group psychotherapy | Billed per participant |
| 90839 | Crisis psychotherapy | First 60 minutes |
| 90833 / 90836 / 90838 | Psychotherapy add-on to an E/M visit (psychiatry) | 16-37 / 38-52 / 53+ minutes |
Take a documented 50-minute session. It falls under 90834, not 90837. Billing 90837 does not match the recorded duration, and that mismatch triggers denials, repayment requests and audit findings. A general EHR billing module built around E/M levels has no reason to flag it. A behavioral health workflow built around the same time thresholds can catch it before submission.
Group therapy adds more. You document one session but bill each participant correctly, sometimes with separate authorizations, while keeping attendance and enrollment straight. A general EHR often has no group billing concept, so staff work claim by claim.
Psychiatry adds a second pattern: an E/M code plus a psychotherapy add-on, with documentation that supports both.
The real cost comparison
A general EHR can carry a lower subscription price. What the pricing page leaves out is staff time spent on template workarounds, denial-rate impact from claims the platform was not built for, and manual compliance tracking. The gap varies with claim volume and payer mix, so calculate your own: clinician hours lost per week, denial rate, and rework hours.
If billing is where you feel the pain, see outsourced medical billing vs software.
Parity, prior authorization and Medicaid rules
Behavioral health claims often involve prior authorizations, session limits and state Medicaid rules that differ from medical billing. Mental health parity laws exist to limit stricter coverage rules for mental health than for medical care, but how they apply depends on the plan and the state. Ask each vendor how it tracks authorizations and visit limits, and how it handles payer-specific rules. Confirm specifics with your payers or a certified billing specialist.
42 CFR Part 2: Consent a General EHR Does Not Model
42 CFR Part 2 protects substance use disorder (SUD) treatment records and requires consent handling beyond standard HIPAA.
The updated Part 2 rule became required on February 16, 2026. Under it, one patient consent can cover future treatment, payment and healthcare operations disclosures. Some uses, including certain SUD counseling notes and any legal proceeding, still need separate, specific consent.
A general EHR built for standard HIPAA does not ask whether a disclosure falls under the broad consent or needs its own authorization, and it usually cannot track which consent covers which disclosure over time.
This matters only if you handle Part 2 records. A counseling practice with no SUD treatment may never need it. For programs that do, tracking consent outside the platform is where the wrong disclosure to the wrong party slips through. The same lesson applies to eConsent software for clinical trials.
Psychiatric Prescribing: EPCS and PDMP
If your practice includes psychiatrists or psychiatric nurse practitioners, prescribing is a separate evaluation. Controlled-substance e-prescribing (EPCS), PDMP checks, medication reconciliation and documentation of risk-benefit discussions should sit inside the workflow, not in a second tool. Where PDMP queries happen outside the EHR, you add steps and documentation gaps. A therapy-only practice can skip this. A mixed prescriber-and-therapist group cannot.
The DevSouq Scope Clarity Session
A free, 30-minute session where you leave knowing the real cost, real timeline, and real risks of your project, whether you ever build with us or not.
Book Your Free Scope Clarity Session →Scheduling, Group Therapy and Telehealth
Behavioral care is recurring. The same client may see you weekly for months, join a group, and bring in family. Behavioral health EHRs schedule recurring series, group rosters and family sessions. General EHRs are built around single visits.
Telehealth is now routine in therapy and psychiatry. Both types offer it, but check that it captures session start and end times, because those feed time-based billing directly. For groups specifically, see our guide to group therapy EHR software.
AI Documentation in Behavioral Health EHRs
Most vendors, both general and specialty, now advertise AI note drafting. Treat it as a feature to test, not a reason to choose a platform. In a demo, check that it:
- Produces your note format (SOAP, DAP or BIRP), not a generic summary
- Keeps psychotherapy notes separate from the progress note
- Handles recording consent and states where audio and transcripts are stored
- Is covered by a BAA
- Always requires clinician review and signature, including any suggested billing codes
Solo Practice vs Group Practice: Different Priorities
| Area | Solo practice | Group practice |
|---|---|---|
| Top priority | Speed: fewer clicks per note | Shared records and consistent documentation |
| Billing | Built in, no second system | Rules and reporting across clinicians |
| Scheduling | Recurring sessions | Groups, rooms and multiple calendars |
| Compliance | Basic HIPAA, Part 2 if applicable | Role-based access, supervision and co-signature |
| Interoperability | Often secondary | Needed when prescribers, therapists and case managers share patients |
A solo clinician who rarely refers out can run well on a lighter system. Once several clinicians share patients, a system that cannot share records becomes the bottleneck.
Specialized, General and Census-Based EHRs: Which Is Which?
If you run residential, inpatient, detox or partial hospitalization programs, “census” matters. Census management means tracking who occupies which bed or program slot today, plus admissions, discharges, transfers, levels of care and shift notes.
| Setting | What you need | Best fit |
|---|---|---|
| Outpatient therapy or psychiatry | Notes, scheduling, time-based billing | Specialized behavioral health EHR |
| PHP / IOP | Group billing, attendance, level-of-care tracking | Specialized, with group and program features |
| Residential / inpatient behavioral | Census and bed management, shift notes, admission and discharge | Specialized with native census, or a hospital EHR |
| Hospital with a behavioral unit | Interoperability with the wider medical record | General or enterprise EHR |
Ask vendors whether census tools are native or an add-on, and whether they connect to clinical notes and billing. A census tool that does not feed billing creates double entry.
Where a General EHR Wins: Interoperability
Be fair to general EHRs here. Large platforms usually have deeper connections to labs, pharmacies and hospital networks. Behavioral health has historically had lower health information exchange participation, although that is improving. Ask each vendor which HIEs, FHIR APIs and referral networks it supports in your state, instead of relying on a general claim.
The other nuance is EMR vs EHR. An EMR is the digital chart inside one practice. An EHR is built to share that record across providers. Where prescribers, therapists and case managers share patients, you need EHR-grade sharing, not an EMR with an export button.
Is There a Free EHR for Behavioral Health? The Tradeoffs
Free and freemium options exist and can suit a new solo practice. Check these before you commit:
- Limits: clinician count, client count, storage or features.
- Paid extras: claims submission, e-prescribing, telehealth, support.
- Data ownership and export: can you leave with a full export?
- BAA: will the vendor sign a HIPAA business associate agreement?
- Part 2 and group billing: often missing at the free tier.
- Growth: what happens when you add a second clinician?
Why Therapy Practices Leave Their EHR
The most common reasons: slow note-writing, denials and billing rework, weak group or recurring scheduling, no outcome tracking, rising per-clinician fees, poor support, and outgrowing a solo-practice tool. Before switching, price the migration (data export, retraining, parallel running), because a bad switch can cost more than the problem it solves. If you are stuck on an aging system, see healthcare application modernization.
Multi-Location Organizations: Keeping Documentation Consistent
Across sites, you need the same templates, treatment-plan structure and billing logic everywhere. Look for organization-level template locking, role-based permissions, required fields, supervisor co-signature, shared reporting and audit trails. Review exceptions monthly. Where no product does this well, the gap is usually workflow, not features.
Can a General EHR Be Customized for Behavioral Health?
Yes, and sometimes it is the right call. You can add templates, fields and third-party tools. It tends to work when the organization is already standardized on one platform across physical and behavioral service lines and has IT staff to maintain it.
It breaks at scale. A solo therapist customizing a general platform solves a small problem. A multi-site organization configuring group billing, treatment plan reviews and Part 2 tracking on a platform with no native concept of them is solving a large one. Budget customization as an ongoing cost, not a one-time setup.
When Neither Option Fits: Build vs Buy
For most solo practices and small groups, this decision is not close. If behavioral health is your main model, specialty software wins on documentation speed, billing accuracy and compliance handling.
The harder case is the organization that has tried both. A specialty platform hits a ceiling on group billing or state reporting. A general EHR carries years of workarounds. The gap is a workflow specific enough that no packaged product fits without compromise.
When a multi-location organization is stuck moving information between disconnected systems, custom software becomes worth evaluating next to the two packaged categories. DevSouq’s custom healthcare software development starts by mapping your workflow, then deciding which system stays authoritative for which information, rather than replacing everything at once. It is not a substitute for a specialty EHR that already fits.
Common Mistakes When Choosing
- Assuming HIPAA compliance covers Part 2. It does not.
- Billing therapy like an E/M visit. Time-based codes depend on documented minutes.
- Choosing on subscription price alone. Add customization, denials and manual compliance work.
- Treating group therapy as a bigger individual session. Documentation and billing are distinct workflows.
- Skipping the EMR vs EHR question when care is split across providers.
How to Choose: Decision Framework
| Your situation | Likely best choice |
|---|---|
| Behavioral health is your main or only model | Specialty behavioral health EHR |
| One service line inside a larger medical organization | Weigh coordination against workflow cost; general or enterprise EHR may fit |
| Residential or inpatient programs | Specialty EHR with native census, or hospital EHR |
| Dedicated IT team on a general EHR already | Customize, and budget it as ongoing |
| Neither category fits even after evaluation | Custom build worth a conversation |
Questions to ask every vendor: Which note formats are native? How are time-based codes validated? How are psychotherapy notes separated? How is Part 2 consent tracked? How does census connect to billing? What can I export if I leave?
Behavioral health EHR evaluation checklist
- Native SOAP, DAP and BIRP notes, not custom-built templates
- Psychotherapy notes stored separately from progress notes
- PHQ-9, GAD-7 and C-SSRS scored and trended over time
- Session start and end times captured for time-based CPT codes
- Group therapy documentation and per-participant billing
- 42 CFR Part 2 consent tracking, if you treat substance use disorders
- EPCS and PDMP inside the prescribing workflow, if you prescribe
- Census and bed management that feeds billing, if you run residential programs
- Role-based access, audit trails and supervisor co-signature
- AI documentation with consent, BAA and clinician sign-off
- Full data export if you leave
- Total cost with customization, denial rate and staff time included
Conclusion
The behavioral health EHR vs general EHR question has a fairly settled answer for most practices: if behavioral health is what you do, software built for it beats a general platform on documentation speed, billing accuracy and compliance handling. General EHRs win when behavioral health is one service line inside a larger medical organization that needs deep interoperability.
The harder case is the organization whose workflow fits neither packaged option. If that sounds like you, a free scope review is a low-commitment way to find out whether a custom approach makes sense. Book your free 30-minute Scope Clarity Session with DevSouq and leave with a real cost, timeline and risk picture, whether you ever build with us or not. For more build-vs-buy decisions, see our healthcare software consulting guide.
Frequently Asked Questions
What is the difference between a general EHR and mental health-specific software?
A general EHR is built around exams, diagnoses, orders and evaluation-and-management billing. Mental health software is built around session notes (SOAP, DAP, BIRP), long-running treatment plans, time-based psychotherapy codes, outcome scales like the PHQ-9, group therapy and, where relevant, 42 CFR Part 2 consent. The data model differs, not just the templates.
Is there a free EHR for behavioral health, and what are the tradeoffs?
Free and freemium options exist, but they usually cap users, billing, telehealth or support, or charge extra for claims and e-prescribing. They can suit a new solo practice. Check data ownership, full export rights, whether the vendor signs a BAA, and what happens when you add a second clinician.
What are the most common reasons a therapy practice leaves its EHR?
Common reasons include slow note-writing, billing and denial problems, weak recurring or group scheduling, no outcome tracking, rising per-clinician fees and poor support. Practices also leave when they outgrow a solo-practice tool or need compliance features such as Part 2 consent. Price the migration effort before switching.
Can a general EHR be customized for behavioral health?
Yes. You can add templates, fields and third-party tools, and it works best for organizations already standardized on one platform with IT support to maintain it. At scale, group billing, treatment plan reviews and Part 2 tracking become staff workarounds. Budget customization as an ongoing cost, not a one-time task.
Do residential and census-based programs need a different EHR?
Usually, yes. Residential, inpatient and PHP programs need bed and census management, admission and discharge tracking, level-of-care documentation and shift notes, which outpatient therapy tools rarely include. Ask whether census features are native or an add-on, and whether they feed clinical notes and billing without double entry.
How can multi-location behavioral health organizations keep documentation consistent?
Use organization-level templates and treatment plan structures, role-based permissions, required fields, supervisor co-signature, shared reporting and audit trails, with one billing logic across sites. Review exceptions monthly. If no product supports this well, the gap is usually workflow, and a custom workflow layer may be worth evaluating.
Which type of EHR is better for interoperability?
Large general EHRs, such as Epic and Oracle Health, usually have broader connections to labs, pharmacies and hospital networks. Behavioral health EHRs often have fewer HIE connections, though this is improving. Ask each vendor which HIEs, FHIR APIs and referral networks it supports in your state rather than relying on general claims.
Is an all-in-one behavioral health EMR worth it?
An all-in-one system helps when it replaces separate tools for notes, scheduling, billing and telehealth without weakening any of them. Verify each module separately in a demo, especially time-based billing and Part 2 consent. If care spans several providers, confirm it shares records like an EHR, not just stores them like an EMR.









